Our cases

Clients about us
Connection to the telematics infrastructure
Connect to the telematics infrastructure: connector, KIM, ePA and e-prescription. What vendors and providers must put in place.
What the telematics infrastructure includes

The telematics infrastructure is the closed network for healthcare providers in Germany. gematik sets the specifications and approves the components. Insurance-data updates (VSDM), KIM, the electronic patient record (ePA), the e-prescription and the electronic sick note (eAU) run on it. A practice PC on the public internet is not this connection. Without an approved access path, an SMC-B for the organisation and an eHBA for the person, the application stays closed. The KBV describes what a contracted practice must keep. Hospitals and pharmacies have their own duties on the same network.
A telematics infrastructure connection does not mean we attach every system to every other system. It means gematik-approved access, cards, a primary system under the KBV rules, and the applications that apply to that organisation. The current crypto migration is on the gematik RSA-to-ECC page. The allowance and the equipment list are at the KBV. Dates on this page are as of early October 2026. They move.
Components: connector, eHBA, SMC-B, KIM
Four pieces carry the connection. If one is missing, more than one function stops. VSDM, the e-prescription, the eAU and the ePA hang on the same chain.
Connector
The connector builds the shielded access and links card terminals to the primary system. Since 1 January 2026 an RSA-only connector cannot reach the network. A single-box device is not built for TI 2.0. A TI gateway uses an approved connector in a data centre.
eHBA
The electronic health professional card identifies the person and creates the qualified signature. Physicians apply through their state chamber. Psychotherapists apply through theirs. Nursing and midwifery use the eGBR. Without a valid eHBA there is no e-prescription and no eAU.
SMC-B
The SMC-B identifies the organisation, not the person. It is ordered from a gematik-approved card provider after an eHBA exists in that organisation. It sits in the card terminal. Without it the site does not connect.
KIM
KIM encrypts messages between providers. The electronic referral letter may only travel over KIM, and so may the eAU. The TI messenger is a different service for short messages and does not replace KIM. The organisation chooses the provider. The module has to sit in the primary system.
A project from our work
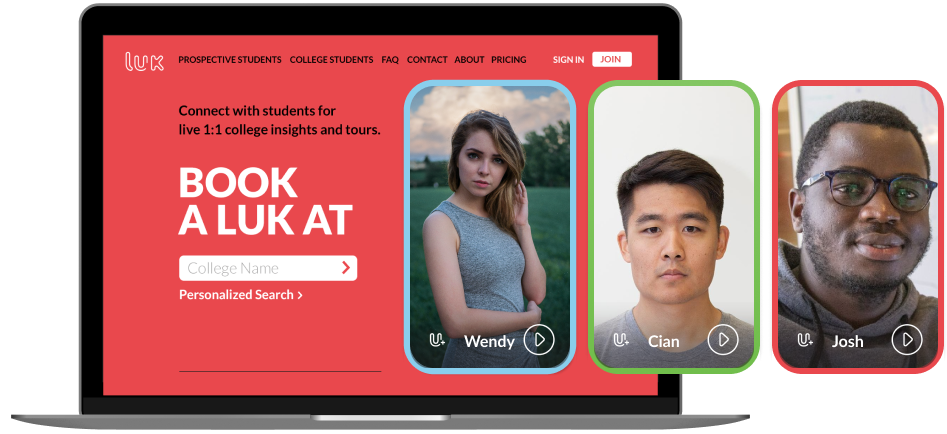
Connect with students for live 1-on-1 college insights and tours
EXPERTISE
Education
TECHNOLOGIES

Integration into systems you already run

The primary system first
The practice system or the hospital system has to support the application in the current version. The KBV rules decide which module a practice needs. We do not write that approval. We build the side that joins the approved system to your workflow.
The primary system first
The practice system or the hospital system has to support the application in the current version. The KBV rules decide which module a practice needs. We do not write that approval. We build the side that joins the approved system to your workflow.

A hospital is a different path
The KBV allowance is for contracted practices, not for a hospital budget. Deadlines, proof and penalties follow other rules there. Delivery inside the hospital sits with software development for hospitals. The same component is not a practice project.

What the organisation decides
Which applications the association exempts for this specialty, which KIM address applies, and whether an on-site connector or a TI gateway fits, is a decision for the organisation and its operator. That belongs with healthcare IT consulting, not with a promise to connect anything.

Records and other systems
When findings from an existing system should reach the ePA, that is an interface to the primary system, not a second record. The technical frame for that work is EHR integrations. The ePA interface stays the one gematik publishes.

Interoperability stays its own page
Profiles between systems do not change a gematik approval. Transport without a TI application is not a telematics connection. The German page planned for that scope is Interoperabilität im Gesundheitswesen. KIM, the ePA and the e-prescription remain the TI applications.

What we do not promise
We do not issue a gematik approval, an SMC-B or an eHBA. We do not say that any software can be attached to the TI. We connect the applications that apply to this organisation to the system you already run.
How the connection runs in the organisation
The order is organisational, not a WTT product. Cards have lead times. gematik’s gateway guide puts the swap itself at one to two hours in good conditions, and longer when a new KIM address is part of it. The association then checks that VSDM runs and that the connector version is valid.
Name the applications
VSDM, KIM, ePA, e-prescription and eAU are the usual set. The association can exempt a specialty from one of them, for example the e-prescription for psychotherapists. That list comes before any order.
OutputApplication list
Name the applications
VSDM, KIM, ePA, e-prescription and eAU are the usual set. The association can exempt a specialty from one of them, for example the e-prescription for psychotherapists. That list comes before any order.
OutputApplication list
Apply for the eHBA
The chamber checks the person. Production, identification and activation take weeks, not an afternoon. Without this card the organisation’s SMC-B cannot follow.
OutputPersonal card
Order the SMC-B
The authorised lead orders the card from an approved provider. The KBV allows about two weeks from application to card and PIN. PIN and card arrive separately.
OutputOrganisation card
Choose the access
An on-site connector or a TI gateway. Both need gematik approval. Since 1 January 2026 an RSA-only connector is out. From 1 October 2026 ECC-only health cards need the current connector version.
OutputApproved access
Update the primary system
The practice or hospital system needs the modules for VSDM, KIM, ePA, e-prescription and eAU in the version the vendor ships. The KBV rules say which module a practice must keep.
OutputCurrent modules
VSDM first
Reading the health card and updating master data is the proof the association sees. Without VSDM the allowance stops and fees can be reduced.
OutputVSDM running
KIM, ePA, e-prescription, eAU
KIM carries the referral letter and the eAU. The e-prescription needs the qualified signature of the eHBA. The ePA is read and filled with the required findings when the insured person has not objected.
OutputApplications
Run and replace
Certificates expire. On gematik’s current page, generation 2.0 terminal cards must stop by 31 December 2026. The next architecture change is TI 2.0, not a quiet extension of the old box.
OutputLive operation
Who issues each component, and what it is for
The left column is the component, the middle the body that issues it, the right the purpose. gematik approval decides which product may enter the telematics infrastructure at all. The table follows the published rules. It is not a decision.
- Not a ranking, only the issuing body
- The purpose of the component
- No approval, no use in the TI
Effort and cost
The amounts are the monthly TI allowance sickness funds pay contracted practices from 1 January 2026, as published by the KBV. They are not a quote from WTT and not a connector vendor’s invoice. One missing application halves the allowance. More than one missing application means no allowance. gematik says the move to an ECC-capable connector or a TI gateway is covered by this allowance.
Practice up to 3
€263.62
per month, 2026
- Four to six doctors: €313.52
- Seven to nine: €359.10
- Above that, €31.70 per further three
- VSDM, ePA, KIM, e-prescription, eAU
- No separate WTT price list
One gap
50%
one application missing
- Up to 3 doctors: then €131.81
- More than one gap: €0
- The association can exempt a specialty
- No VSDM can also cut fees
- KV Baden-Württemberg states 2.5 percent
Besides that
Cards
weeks, not the allowance
- eHBA via the chamber, several weeks
- SMC-B often about two weeks
- A gateway swap often one to two hours
- Hospitals: not this allowance
- No fixed price for an approval
What clients say
INDUSTRY RECOGNITION


Luklabs
Acting CEO
The team is smart, creative, nice, calm, and professional, and they are problem solvers.
WTT Solutions paid attention to details. Most of their first iterations were very close to our intended designs. Consequentially, we didn’t have to do a ton of revisions in the QA phase.
I greatly enjoyed working with them.


Connecting the electronic patient record
Since 15 January 2025 people with statutory insurance receive an ePA unless they have objected. Nationwide operation has run since 29 April 2025. Since 1 October 2025 providers must use the ePA and file the required data. The source is the federal health ministry.

Access through the health card
Inserting the card opens the care context. The ministry says a pharmacy then has three days of access. The insured person can shorten, extend or block access.

What must be filed
Reports, laboratory results, imaging and the electronic referral letter, where they were processed electronically and there is no objection. Further data, such as the eAU, only on request. The list is in the social code, not in a project contract.

The primary system has to be able
A practice whose system does not yet ship the ePA cannot meet the duty with a second store. The KBV tracks which versions are delivered. We connect the system you have. We do not replace the record.

Medication list and plan
E-prescription data flows into the ePA medication list. The electronic medication plan is the next stage. Published dates for it have moved. gematik names the current one, not this page.

An objection ends the duty
If the insured person objects, nothing is filed. That is not a technical fault and not a reason to build a second record beside it. The organisation records the objection under its own rule.
The e-prescription in the practice
01

Mandatory since 1 January 2024
Physicians must prescribe prescription-only medicines charged to statutory insurance as an e-prescription. Narcotics and named special cases are excluded. gematik describes the service.
02

Signed with the eHBA
The prescription is signed with a qualified electronic signature. The pharmacy checks that signature when dispensing. A printout can support redemption. It does not replace the signature. Without an ECC-capable eHBA this step stops.
03

Redemption
Insured people redeem with the health card, in the fund’s app, or with a printout. For a statutory-insurance redemption gematik names 28 days. After that it is not an open paper prescription.
04

DiGA on the same prescription
Digital health applications can be prescribed as an e-prescription since October 2025. That prescription goes to the sickness fund, not to the pharmacy. The prescription does not change the product’s class.
05

What has to be in the practice
A current connector or TI gateway, an SMC-B, an eHBA, a card terminal and a primary system with the e-prescription module. If the module is missing, a manual PDF does not help. The KBV can exempt specialties that do not usually prescribe.
06

No promise that every prescription goes through
We do not promise that every prescription completes. The signature, the service and the pharmacy system sit outside our contract. We connect the prescribing system to the components that apply.

Deadlines, duties and penalties
gematik’s migration page, as updated on 9 September 2026. The KBV allowance, as of 1 January 2026. gematik says the dates can change. A fee cut is set by the association, not by WTT. KV Baden-Württemberg states 2.5 percent while VSDM is not running.

1 January 2026
No TI access with an RSA-only connector. The primary system and KIM had to support ECC by the end of 2025.

30 June 2026
Deadline to replace generation 2.0 eHBA and SMC-B cards without ECC. Without a valid card, signature and access fail.

1 October 2026
Health cards issued from this date are ECC-only. The connector has to be on the current product version.

14 October 2026
gematik sets the RSA SMC-B authority to revoked on the trust list. Further RSA blocks follow in November.

31 December 2026
Generation 2.0 terminal cards must not be used after that. The terminal needs generation 2.1.

ePA and e-prescription
E-prescription duty since 1 January 2024. Duty to use and fill the ePA since 1 October 2025.

Allowance
One missing application halves the monthly TI allowance. Several missing applications remove it.

Fees
Without VSDM, associations cut fees. The local rule applies, not a number on this page treated as a ruling.


TI 2.0: what changes
TI 2.0 moves access to zero trust: no access is assumed, each one is checked. gematik planned productive VSDM 2.0 with proof of patient presence for July 2026. In the third-quarter 2026 roadmap, data as of 24 September 2026, proof of patient presence and connector PTV6 are in hypercare, and zero-trust access stage 2 is still in development. All TI services are planned to move by 2029. The KBV will switch off its secure network on 31 October 2028. A single-box connector is not provided for in TI 2.0. The approved path without an on-site box today is the TI gateway. The plan is in the gematik portal and can move.
 OpenAI
 Google Gemini
 Anthropic Claude
 LangChain
 LlamaIndex
 Perplexity API
 RAG / Pinecone / Qdrant


 PostgreSQL
 MySQL
 MongoDB
 Redis
 Docker
 Kubernetes
 Terraform
 GitHub Actions


